
INTRODUCTION
Age-related macular degeneration (AMD) is a chronic retinal disease and one of the leading causes of irreversible central vision loss among the elderly in developed countries [1]. The number of individuals affected by AMD worldwide is projected to increase steadily as the population ages, making this condition a major public health challenge [2]. The disease damages the macula, and the subsequent loss of central vision severely restricts patients’ ability to perform activities of daily living, reducing their quality of life [3].
AMD is divided into two primary forms: dry (non- exudative) and wet (exudative/neovascular). Dry AMD accounts for the majority of cases and progresses slowly, leading to geographic atrophy in its advanced stage. Conversely, wet AMD is characterized by pathologic neovascularization and is responsible for sudden, severe vision loss [4].
Clinical staging classifies AMD into three main categories: early AMD (defined by the presence of medium drusen), intermediate AMD (characterized by large drusen and/or retinal pigmentary abnormalities), and advanced AMD, which encompasses either geographic atrophy secondary to the dry form or pathologic neovascularization in the wet form.
The diagnosis of AMD relies primarily on structural and functional imaging techniques, including optical coherence tomography (OCT), OCT angiography (OCTA), fluorescein angiography, and fundus autofluorescence (FAF) [5]. Functional assessments, such as visual acuity testing and dark adaptation testing, are also used. However, they do not always enable the early detection of disease progression [6]. Available treatment options remain limited, with effective therapies currently confined to the wet form of AMD. Management options for dry AMD remain limited, although complement inhibitors have recently been approved in the United States to slow the progression of geographic atrophy. This therapeutic gap highlights the urgent need for novel diagnostic tools to identify individuals at risk of progression and to monitor the efficacy of future therapies [7, 8].
In recent years, a special role has been attributed to biomarkers, which can complement conventional imaging modalities [9–11]. Structural biomarkers, assessed via imaging, include, among others, drusen size and distribution, retinal layer thickness on OCT, the presence of abnormal autofluorescence signals, and OCTA parameters [12–20]. Modern imaging techniques, particularly spectral-domain optical coherence tomography and swept-source optical coherence tomography, enable the detection of even minor structural changes, such as individual hard drusen, prior to the development of clinically manifest AMD. Fundus photography allows for the monitoring of morphological changes, while high-resolution imaging enables the detection of early abnormalities that precede the onset of clinical symptoms [21–24]. Structural biomarkers play a significant role in predicting the progression from intermediate to advanced AMD [25–29]. At the same time, functional biomarkers, such as impaired dark adaptation or reduced retinal sensitivity assessed by micro- perimetry, represent a valuable tool in evaluating the early stages of the disease [30].
However, particular attention should be given to molecular biomarkers, as they provide direct insight into the pathophysiological mechanisms underlying AMD. Unlike structural and functional biomarkers, which reveal the effects of the disease at the anatomical and clinical levels, molecular biomarkers allow for the assessment of inflammatory, oxidative, and metabolic alterations occurring in both the retina and throughout the body [9–11]. They can serve as early risk indicators, progression markers, and tools for monitoring treatment response.
Among the most extensively studied molecular biomarkers in AMD are inflammatory proteins and mediators. Elevated serum concentrations of C-reactive protein and interleukins, including interleukin-6 (IL-6), have been reported in patients, indicating the involvement of inflammatory processes in disease progression [9, 10]. Matrix metalloproteinases (MMPs) and tissue inhibitors of metalloproteinases (TIMPs) also show substantial diagnostic utility. Altered levels of these substances are associated with extracellular matrix remodeling and drusen formation. Another significant biomarker is amyloid-β, which deposits in drusen and is associated with the activation of a local inflammatory response in the retinal pigment epithelium (RPE) [11].
The second group of molecular biomarkers consists of microRNAs (miRNAs), which are short, non-coding RNA molecules that regulate gene expression. Studies have demonstrated altered expression profiles of various miRNAs in the serum of AMD patients, including miR-27a-3p, miR-29b-3p, miR-195-5p, and miR-146a [9, 10]. These molecules are involved in regulating inflammatory processes, angiogenesis, and apoptosis, and their dysregulation may indicate disease activity even before clinical changes appear. Consequently, miRNAs are recognized as potential diagnostic and prognostic biomarkers [11].
Genetic factors also represent an important category of biomarkers. The best-documented role in AMD pathogenesis is attributed to polymorphisms in the CFH and ARMS2/HTRA1 genes, which increase disease risk and accelerate progression [9, 11]. Understanding a patient’s genetic profile not only enables assessment of AMD risk but also provides deeper insight into the mechanisms leading to macular damage.
Additionally, research on molecular biomarkers includes proteomic analyses of the aqueous humor, vitreous humor, and tear film, which reveal changes in the expression of numerous proteins associated with oxidative and inflammatory processes [12–16]. Although these methods remain largely in the research phase, the findings suggest that there is a broad range of molecules which may be useful for diagnosing and monitoring AMD.
In summary, molecular biomarkers in AMD encompass proteins associated with inflammatory processes, oxidative stress factors, extracellular matrix enzymes, miRNAs, and genetic variants. They may play a vital role in detecting early stages of the disease, assessing the risk of its progression, and determining patient eligibility for therapy. Integrating them with imaging and functional biomarkers offers the prospect of developing complex diagnostic models that could ultimately contribute to improving patient care in AMD [30].
AIM
The aim of this review was to analyze the current state of knowledge on molecular biomarkers useful for the early detection and monitoring of AMD.
To address this primary objective, the following specific aims have been defined:
To present the pathogenic mechanisms of AMD that serve as the basis for the search for molecular biomarkers.
To characterize established and potential molecular biomarkers (genetic, protein, metabolomic, miRNA, and others) associated with individual stages of AMD.
To evaluate the utility of these biomarkers in the diagnosis, prognosis, and monitoring of disease progression, with a particular focus on their potential clinical applications.
To identify current research limitations and future prospects regarding the integration of molecular biomarkers into ophthalmic practice.
MATERIAL AND METHODS
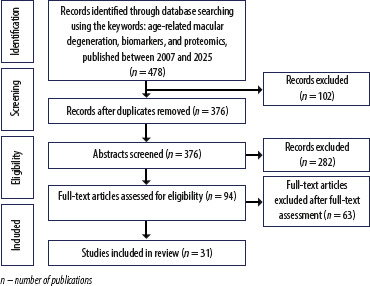
A literature review was conducted to evaluate the biomarkers used in the diagnosis and monitoring of AMD. The search was performed across the PubMed, Scopus, and Web of Science databases, spanning publications from 2007 to 2025 and utilizing keywords and Medical Subject Headings terms: “age-related macular degeneration”, “biomarkers”, and “proteomics”. The terms were combined using Boolean operators (“AND”, “OR”). The analysis included full-text, original clinical and observational studies involving adult patients with AMD. Animal studies, case reports, conference proceedings, and publications without full-text access were excluded. The study selection process involved screening titles and abstracts, followed by full-text analysis and methodological quality assessment using standardized tools to minimize the risk of bias. The review protocol was not registered, which is acceptable for systematic narrative reviews. Data extraction was performed independently by two investigators, with any discrepancies resolved through consensus. The extracted data focused on the type of biomarkers, the research methodologies employed, and the clinical significance of the findings. A total of 31 publications were selected for analysis, and the selection flow is illustrated in the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) diagram (Figure 1). Due to methodological heterogeneity and the absence of comparable effect measures, this review is narrative in nature; a meta-analysis was not performed.
RESULTS
A total of 31 publications were included in the analysis. The studies covered several categories of molecular biomarkers: genetic, proteomic, metabolic, amyloid, miRNA, autoantibody, and metalloproteinase markers, as well as imaging biomarkers. Genetic studies most frequently reported gene variants in the complement system (including CFH and C3) and the ARMS2/HTRA1 region, which are associated with an increased risk and faster progression of AMD. Proteomic analyses and ocular fluid assessments revealed altered concentrations of inflammatory proteins and amyloids, while metabolomic studies pointed to disruptions in lipidomics and amino acid metabolism that could enable differentiation between disease stages. miRNA profiles (including miR-27a-3p, miR-29b-3p, and miR-146a) are emerging as promising markers that regulate inflammation and angiogenesis. MMPs and TIMPs demonstrated potential as biomarkers to differentiate between exudative AMD and geographic atrophy. Most included studies were preliminary, with limitations including small sample sizes, methodological heterogeneity, and a lack of independent validation. The integration of molecular biomarkers with imaging data (OCT/OCTA) appears to be the most promising direction for developing future diagnostic panels (Table I).
Table I
Summary of biomarker studies in age-related macular degeneration (AMD)
| Biomarker type | Author and year of publication | Clinical role/ significance | AMD type | Methodology | Main findings |
|---|---|---|---|---|---|
| Genetic | Grassman (2015) [4]; Huang (2024) [26]; de Breuk (2021) [27]; Bhumika (2024) [24] | Identification of risk genes (CFH, ARMS2, C3, HTRA1), assessment of heritability and predisposition | Both | GWAS, association analysis, genotyping | Polymorphisms in complement and lipid metabolism genes are key to AMD risk; population differences hold diagnostic significance |
| Proteomic | Gu (2010) [25]; Yuan (2010) [8]; Guo (2023) [19]; Guymer (2011) [5] | Detection of protein changes in plasma, ocular fluids, and urine | Both | LC-MS/MS, proteomic analysis | Alterations in inflammatory, structural, and amyloid proteins can serve as biomarkers for AMD progression and differentiation |
| Metabolic/ lipid-related | Laíns (2018) [13]; Reynolds (2010) [14]; Li (2023) [28]; Li (2025) [18] | Lipids and metabolites as markers for early detection and progression | Both/ early | LC-MS, metabolomic analysis, Mendelian randomization | Disruptions in lipid and amino acid metabolism differentiate AMD stages and may have a protective significance (HDL) |
| miRNA/ non-coding RNA | Szemraj (2015) [6]; Ragusa (2013) [7]; Cruz-Aguilar (2023) [29] | Regulation of gene expression, inflammation, and angiogenesis | Both | RT-qPCR, miRNA analysis, bioinformatics | miR-21, miR-146a, miR-155, and lncRNAs modulate inflammatory processes and neovascularization, making them potential biomarkers and therapeutic targets |
| Autoimmune (autoantibodies) | Morohoshi (2012) [9] | Potential regulators of neovascularization | Exudative | ELISA | Presence of autoantibodies may influence angiogenesis and the clinical course of exudative AMD |
| Imaging (OCT, functional) | Thiele (2020) [15]; Sleiman (2017) [16]; Niu (2016) [17]; Lai (2019) [21]; Vujosevic (2011) [3] | Early and non-invasive indicators of progression and treatment evaluation | Dry/ exudative/ intermediate | OCT, microperimetry, AI analysis | RPE thickness, photoreceptor layer, and retinal integrity predict progression; OCT biomarkers support the evaluation of anti-VEGF therapy |
| Amyloid | Lashkari (2020) [11] | Markers of geographic atrophy | Dry (GA) | Plasma amyloid analysis | Amyloid biomarkers may predict the development of geographic atrophy (GA) |
| MMP/TIMP | Krogh Nielsen (2019) [12] | Differentiation between CNV and GA | Both | Immunological analysis | TIMP imbalances differentiate AMD subtypes and may serve as a biomarker for the exudative form |
| Multifactorial/reviews | Fang (2021) [1]; Amini (2023) [31]; Gao (2025) [22] | Overview of biomarkers and molecular mechanisms | Both | Systematic and narrative review | AMD is a multifactorial disease; integrating genetic, proteomic, and imaging biomarkers improves diagnostic accuracy |
[i] AI – artificial intelligence; AMD – age-related macular degeneration; CNV – choroidal neovascularization; ELISA – enzyme-linked immunosorbent assay; GA – geographic atrophy; GWAS – genome-wide association study; HDL – high-density lipoprotein; LC-MS – liquid chromatography–mass spectrometry; LC-MS/ MS – liquid chromatography–tandem mass spectrometry; lncRNA – long non-coding RNA; miRNA – microRNA; MMP – matrix metalloproteinase; OCT – optical coherence tomography; RPE – retinal pigment epithelium; RT-qPCR – reverse transcription quantitative polymerase chain reaction; TIMP – tissue inhibitor of metalloproteinases; VEGF – vascular endothelial growth factor
DISCUSSION
AMD is a chronic retinal disease and one of the leading causes of irreversible vision loss in older adults [1]. Despite significant advances in imaging diagnostics and treatment of the exudative form of the disease, early detection and effective monitoring of AMD progression remain major clinical challenges. In recent years, research into molecular biomarkers has intensified, with the potential to enable earlier identification of individuals at risk, as well as improve assessment of treatment efficacy and prediction of disease course.
The best-documented role in AMD pathogenesis is attributed to polymorphisms in the CFH and ARMS2/HTRA1 genes, which increase disease risk and accelerate progres- sion [9, 11]. The Y402H variant of the CFH gene is particularly important, as it may increase the risk of developing AMD by 2- to 7-fold, depending on the population and additional environmental factors. Variants in the ARMS2/HTRA1 region, in turn, are associated with both increased risk of AMD onset and faster progression to advanced stages. Numerous studies confirm their significant impact on disease risk and progression. The CFH polymorphism is considered one of the key genetic markers, and its presence may increase susceptibility to AMD several-fold. Incorporating such markers into predictive panels improves the identification of high-risk individuals, although their diagnostic value in isolation remains limited. For this reason, there is a growing trend toward combining genetic markers with environmental factors (such as smoking, diet, and exposure to oxidative stress) and other biological parameters.
Studies have revealed complex alterations in the protein profiles of serum and ocular fluids in patients with AMD. Elevated serum concentrations of C-reactive protein and interleukins, including IL-6, have been reported in patients, indicating the involvement of inflammatory processes in disease progression [9, 10]. At the same time, increased levels of proinflammatory cytokines and angiogenic factors, such as vascular endothelial growth factor (VEGF), correlate with progression of the exudative form. Despite promising results, most of these markers show low specificity, as similar changes are also observed in other inflammatory retinal diseases. For this reason, protein biomarkers require further validation in large, prospective patient cohorts.
Emerging areas of research include the analysis of miRNAs. Studies have demonstrated an altered expression profile of numerous miRNAs in the serum of AMD patients, including miR-27a-3p, miR-29b-3p, miR-195-5p, and miR-146a [9, 10]. These molecules are involved in regulating inflammatory processes, angiogenesis, and apoptosis, and their dysregulation may indicate disease activity even before clinical changes appear. As such, miRNAs are considered potential diagnostic and prognostic markers [11].
At the same time, metabolomics and lipidomics are developing, providing insight into metabolic disturbances within RPE cells. Oxidative stress plays a significant role in the pathophysiology of AMD. An imbalance between the synthesis and clearance of reactive oxygen species is the main source of increased oxidative damage to the RPE [31]. In addition, lipid profiles and lipid peroxidation products may reflect the degree of oxidative damage and the activity of inflammatory processes.
Extracellular vesicles represent another promising area of research, as they carry protein and RNA molecules reflecting the state of retinal cells. Their isolation from blood or aqueous humor may, in the future, enable non-invasive assessment of pathological processes within the macula.
Despite significant progress, the implementation of molecular biomarkers into clinical practice faces numerous challenges. The most important of these include:
lack of standardization in sample collection and analysis,
small study populations,
heterogeneous clinical criteria for AMD,
lack of independent validation studies.
Many reports are either preliminary in nature or based on the analysis of single markers, which limits their prognostic value. There is increasing emphasis on the need to develop composite biomarker panels that combine genetic, proteomic, metabolomic, and imaging data. Such a multidimensional approach could significantly increase diagnostic and prognostic accuracy.
From a clinical practice perspective, molecular biomarkers may in the future serve several key functions:
enabling the identification of individuals at high risk of developing AMD,
supporting treatment selection and monitoring of treatment response,
providing instruments for evaluating the efficacy of new drugs in clinical trials.
Combining biomarkers with imaging modalities (OCT, OCTA, FAF) could create a comprehensive diagnostic- prognostic system for individualized patient care.
There is also growing interest in the use of artificial intelligence (AI) and machine learning in the analysis of AMD biomarkers. Emerging models integrate OCT/OCTA imaging with molecular and genetic data to predict disease progression and response to anti-VEGF therapy. AI-based algorithms may enable the creation of multidimensional diagnostic panels allowing for more precise assessment of AMD progression risk and personalization of therapy.
In summary, current research highlights the significant potential of molecular biomarkers in the diagnosis and monitoring of AMD; however, their routine clinical application requires further validation and standardization. Future approaches will likely focus on multiparametric models integrating diverse biological and clinical data, enabling earlier detection and more effective disease management.
LIMITATIONS AND FUTURE PERSPECTIVES
The review has several limitations. First, most of the analyzed studies include small patient groups, which limits the statistical power of their findings. Second, there is considerable methodological heterogeneity in terms of clinical definitions of AMD, sample collection procedures, and the analytical techniques employed, including reverse transcription quantitative polymerase chain reaction, liquid chromatography–mass spectrometry, and proteomic analysis. Third, many publications lack data on the validation of biomarkers in independent cohorts. Another limitation is that some data are derived from cross-sectional studies, making it difficult to establish clear cause-and-effect relationships. Therefore, prospective, multicenter clinical studies are needed, using integrated diagnostic models that incorporate molecular, imaging, and functional biomarkers.
CONCLUSIONS
AMD is a disease with a complex, multifactorial pathogenesis in which inflammatory processes, oxidative stress, dysregulation of the complement system, and genetic factors play critical roles. The complexity of these mechanisms makes the identification of a single, universal biomarker unlikely.
Molecular biomarkers (genetic, protein-based, metabolomic, and miRNA) represent a promising tool for early AMD diagnosis and monitoring. In particular, variants of the CFH gene, elevated VEGF levels, and altered expression of selected miRNAs demonstrate strong prognostic and diagnostic potential.
Despite a growing number of studies, most proposed biomarkers remain in the experimental stage, and their clinical utility requires further validation in large, prospective, multicenter studies. Standardization of methods for collecting, storing, and analyzing biological samples is also paramount.
The most promising direction for future development is the integration of different types of biomarkers (genetic, proteomic, metabolomic) with clinical and imaging data (OCT, OCTA), which may lead to the creation of comprehensive predictive models and personalized treatment strategies.
Ultimately, implementing validated molecular biomarkers into clinical practice could in the future enable earlier AMD detection, more effective monitoring of disease progression, and optimized therapy, representing a major step toward precision medicine in ophthalmology.








